
Uncategorized
Retatrutide vs semaglutide
Sep
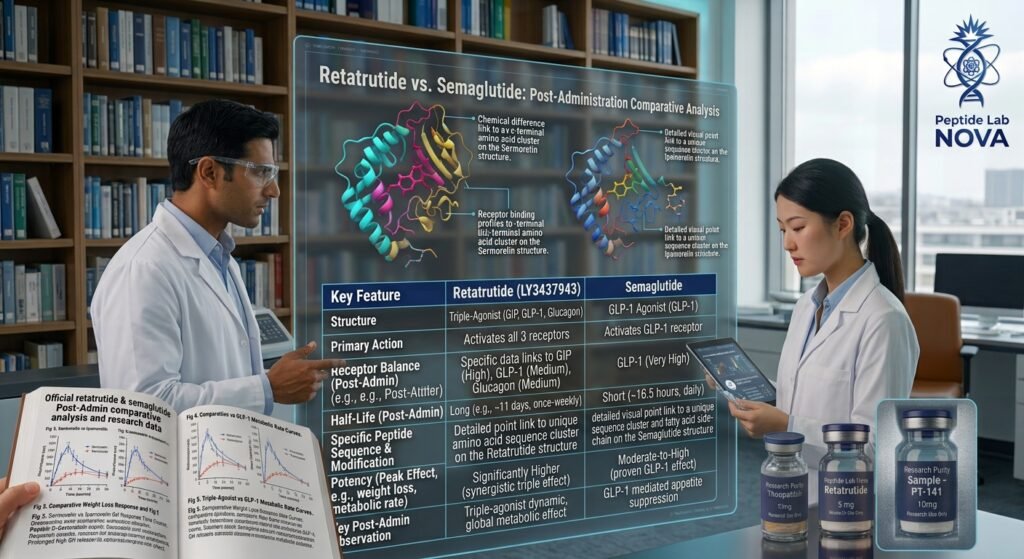
Few keyword comparisons in peptide research supply generate as much lab-side interest as retatrutide vs semaglutide, and the reason is straightforward: both are synthetic peptides that act on metabolic signaling pathways, both are ordered by the same kinds of research teams, and both are frequently discussed in the same breath even though they are chemically and pharmacologically distinct compounds. Retatrutide is a much newer triple-receptor agonist studied in metabolic and energy-balance research, while semaglutide is a mature, closely characterized GLP-1 receptor agonist with a large body of published work behind it. For a laboratory that needs reproducible, defensible results, understanding exactly what each peptide is, how it is studied, what the certificate of analysis can and cannot prove, and how to handle both compounds correctly matters long before the first vial is opened. This guide walks through both compounds in plain, practical language for research buyers only: what each peptide is, why the comparison matters in the lab, how the studied mechanisms differ, what the published literature actually covers, how purity and documentation change the picture, and how to reconstitute and store both compounds. Everything on this page is written for laboratory research use; PeptideLabNova supplies peptides exclusively for research purposes, not for human consumption.
Retatrutide vs Semaglutide: What Each Compound Is
Retatrutide is a synthetic peptide that was designed as a triple agonist: it is intended to engage three distinct receptor systems — the GLP-1 receptor, the GIP receptor, and the glucagon receptor — from a single molecule. Its amino acid sequence is derived from the human incretin peptides, and published studies describe it as having a cyclized (Z)-configured core that contributes to its metabolic stability. The peptide is studied in the context of energy balance, body-weight regulation, and metabolic signaling, and early clinical data reported aggressive weight-loss outcomes that made it one of the most-discussed investigational peptides in recent years. In research supply catalogs, retatrutide is generally offered as a lyophilized peptide that must be reconstituted before use, exactly like other synthetic peptides.
Semaglutide is a synthetic 31-amino-acid peptide based on the glucagon-like peptide-1 sequence, modified for resistance to enzymatic degradation: it replaces two amino acids with non-coded alpha-aminoisobutyric acid residues and carries a C-terminal amide, changes that sharply extend its stability in biological fluids. It is a selective GLP-1 receptor agonist and is one of the most extensively studied peptides in metabolic research, with a deep body of published literature spanning receptor pharmacology, pharmacokinetics, and downstream signaling. Semaglutide is typically supplied in research vials as a lyophilized peptide, and because of its documented sensitivity to moisture and pH, it demands disciplined reconstitution and storage practices in the laboratory.
The practical point for a research buyer is that retatrutide vs semaglutide is not a two-way choice between closely related reagents. One compound is a multi-receptor tool for probing integrated metabolic signaling; the other is a single-receptor reference with an enormous evidentiary base. Studies that call for a well-characterized GLP-1 protocol may be better served by semaglutide, while experiments designed to test combinatorial signaling may need the triple-agonist architecture of retatrutide. Matching compound to question is the first step of reproducible work.
Why Laboratories Compare Retatrutide vs Semaglutide
Research buyers frequently request a direct comparison of retatrutide vs semaglutide because the two peptides sit at opposite ends of the metabolic-research maturity curve, and that difference drives very different experimental decisions. A laboratory planning a multi-week energy-balance study needs to know which compound has dosing conventions reported in the literature, which one has published stability data, and which one will produce results that reviewers can connect to prior work. Semaglutide wins on precedent: thousands of published papers describe its receptor pharmacology, its signaling cascade, and its stability behavior, so a lab that follows those protocols is building on a documented foundation. Retatrutide, by contrast, is still accumulating its literature, so researchers using it must be more explicit about purity, reconstitution, storage, and dose justification in their methods sections.
The comparison also matters because the two peptides engage different receptor networks, and each network is tied to different downstream endpoints that a laboratory may measure: cyclic AMP accumulation for GLP-1 receptor engagement, calcium flux and insulin-promoting pathways for GIP receptor signaling, and glycogenolytic and gluconeogenic outputs for glucagon receptor activation. A laboratory that needs a clean single-receptor signal will choose a selective agonist such as semaglutide; a laboratory that wants to observe how multiple signals integrate will choose the multi-agonist. Documenting why one was selected over the other is part of good experimental hygiene and appears directly in the introduction of the final manuscript.
Finally, the practical supply picture differs. Because semaglutide is long established, more reference data and stability literature exist, and comparability across batches is easier to defend. Retatrutide is newer, so the documentation burden — proof of synthesis, HPLC purity, mass-spectrometry confirmation, and batch consistency — falls more heavily on the vendor and on the buyer who must verify it. Every peptide supplied by PeptideLabNova is research-use only, and the lab reports page explains how to read the analytical documentation that accompanies each batch.
How the Mechanisms Differ in Practice
The mechanism story is where retatrutide vs semaglutide stops being a naming question and becomes a bench question. Semaglutide is a selective agonist engineered for the GLP-1 receptor alone; in binding studies it shows high affinity for that receptor, and its signaling cascade converges on adenylate cyclase activation and elevated cyclic AMP in GLP-1 receptor-expressing tissues. That amplification drives the downstream effects that dominate the published literature: insulin secretion in response to glucose, suppression of glucagon output from the pancreas, and signals that propagate to appetite-regulating centers. Because the compound is selective, its receptor pharmacology is relatively clean to interpret, which is precisely why it is used as a reference tool in so many studies.
Retatrutide is designed to engage three receptors from one sequence, but it is not a mixture of separate peptides. Its pharmacology depends on how well the single molecule fits each of the three receptor binding pockets, how the resulting complexes differ in residence time, and how the downstream pathways interact inside the same cell. The published mechanism literature describes it as combining GLP-1 receptor agonism with GIP receptor agonism and glucagon receptor agonism in one molecule, which creates an experimental environment where multiple second messengers are active simultaneously. For a research team, that means the signal you observe is the integrated product of three pathways, not the output of one — an important distinction when interpreting dose-response curves.
The dose-response shape is also different in practice. A selective agonist such as semaglutide tends to produce a familiar sigmoidal curve in receptor-activation assays, which makes EC50 comparisons across laboratories meaningful. A triple agonist such as retatrutide can produce apparent response curves that reflect the composite of multiple receptors, so the shape of the curve, and its plateau, may differ depending on which cell model is used. Labs that compare the two compounds side by side should therefore report the assay system, the receptor expression profile of the cells, and the normalization method, or the comparison will not be interpretable.
What the Published Literature Actually Covers
Any honest discussion of retatrutide vs semaglutide has to acknowledge that the two compounds do not have comparable bodies of published evidence. Semaglutide research is extensive: it is covered by an enormous number of papers indexed on the public databases, including receptor-binding studies, pharmacokinetic characterizations, stability analyses, and a very long tail of metabolic outcome studies. Searching the literature by the compound name plus the relevant pathway terms returns a dense bibliography, and most of what a laboratory needs to design a semaglutide protocol — doses, vehicles, reconstitution conventions, assay conditions — can be found directly in the literature.
Retatrutide is newer, so its public bibliography is smaller and more concentrated. The papers that do exist come mostly from the discovery and early clinical-evaluation pipeline, and they cover the design rationale of the triple agonist, its receptor activity profile, and early outcome data. Because the peptide is still early in its research lifecycle, laboratories must be more careful: fewer independent groups have reproduced the work, and methods details in the early papers may not translate directly to in-vitro or small-animal protocols. The responsible approach is to treat retatrutide publications as a starting point and to validate purity, identity, and handling conditions locally.
For practical searching, the PubMed index for retatrutide and the PubMed index for semaglutide give a quick, reproducible way to see how the two bibliographies compare, and adding pathway terms such as glucagon-receptor agonism narrows the search to mechanism-focused papers. A well-built reference list is one of the cheapest forms of experimental rigor, and it costs nothing but search time.
Peptide Form, Purity and Documentation
Both peptides reach the research bench as lyophilized solids, most commonly as peptides supplied in sterile vials after HPLC purification. Purity is the first thing a conscientious buyer checks, and it is usually expressed as HPLC area percent from a chromatographic trace. For any peptide intended for experiments where dose matters, an HPLC-certified purity of 98% or higher is a reasonable expectation, and the certificate of analysis should state the analytical method, the observed purity, the batch number, and the date of analysis. The how to read a COA guide explains each field so that nothing is left to assumption.
Identity confirmation is just as important as purity. HPLC alone tells you that the sample is mostly one compound; it does not prove which compound it is. Responsible suppliers pair HPLC with mass-spectrometry confirmation, and the certificate should report the observed molecular weight and the expected molecular weight of the peptide. Any substantial gap between the two is a red flag, because the peptide might not be the peptide named on the label. A laboratory that orders retatrutide and never verifies the observed mass is effectively trusting the label, and trust is not an analytical method.
The documentation question also extends to the comparison itself. If the goal is an experiment that contrasts retatrutide vs semaglutide, both peptides should arrive with equivalent documentation: same purity floor, same identity confirmation, same batch traceability. If one variety is purchased from a vendor with full mass-spec documentation and the other from a source that provides only HPLC area, the comparison is confounded before it starts. Buy both from suppliers that can show their evidence, keep the certificates with the experiment records, and record the batch numbers in the methods section of any manuscript.
Reconstitution and Storage for Both Compounds
Lyophilized peptides are generally most stable when they stay dry and cold, and both retatrutide and semaglutide follow the same broad rules: store the sealed vial desiccated and frozen, ideally at -20°C or below, and protect it from repeated freeze-thaw cycles. Moisture is the enemy of peptide stability because it enables hydrolysis and microbial activity; every time a vial is opened, ambient humidity has a chance to enter. A dedicated desiccator, or a freezer box with desiccant and a temperature log, is the standard answer for long-term storage. The reconstitution and storage guide covers this in detail for research buyers.
Reconstitution practice matters because both peptides are supplied as lyophilized powder with a stated peptide content per vial. The correct procedure is to record the exact volume of solvent added, the solvent composition, and the time of reconstitution for every vial, because the usable concentration depends entirely on the peptide content stated on the certificate, not on the gross mass in the vial. A common error is to calculate concentration from total vial fill weight while ignoring counterions and residual moisture; the certificate’s peptide-content figure is the number that belongs in the calculation.
Once reconstituted, working aliquots should be prepared immediately, flash-frozen, and stored so that each aliquot is thawed only once. Retrospective troubleshooting of an unexplained experiment is dramatically easier when the storage log shows that every aliquot followed the same protocol. For a compound as well documented as semaglutide, deviations from published stability guidance are hard to defend in a manuscript; for a newer compound such as retatrutide, disciplined storage is the only way to keep batch-to-batch variation from being attributed to the molecule itself.
Which One Should Your Laboratory Choose?
There is no universal winner in retatrutide vs semaglutide; there is only the right tool for the question. If the experiment is designed around GLP-1 receptor signaling, and the literature base, dose conventions, and stability data of a mature peptide are advantages, semaglutide is the conservative, well-justified choice. If the research question concerns how multiple incretin and glucoregulatory signals integrate, or if the laboratory specifically wants to probe triple-agonist pharmacology, retatrutide is the compound designed for exactly that question, with the caveat that the documentation burden is higher.
Budget and supply reliability also enter the decision. A mature peptide with broad distribution can usually be restocked with short lead times and consistent batch documentation. A newer peptide may be supplied by fewer vendors, with longer lead times, and the buyer should confirm that the certificate of analysis actually travels with the shipment and covers the correct batch number on the label. Buyers who depend on a stable reference across a long study series should weigh the supply continuity risk of a newer compound carefully.
When in doubt, run the decision on paper first: state the research question, list the receptor and signaling requirements, and then check which compound’s published protocols match the planned methods. If the paper exercise points to one compound, the bench work will almost always confirm it. The what are research peptides page is a useful primer for teams that are new to ordering this category of reagent.
Buying Lab-Tested Retatrutide vs Semaglutide
When the decision is made, procurement should be treated as part of the experimental design. Both compounds are available from research suppliers such as PeptideLabNova as lyophilized, research-use-only peptides, and the retatrutide listing and the semaglutide listing show the documentation that responsible vendors provide with each batch. The purchase record should capture the product name, batch number, stated purity, peptide content per vial, date received, and the certificate of analysis, because all of these fields eventually belong in the methods section and the laboratory notebook.
A useful habit is to request or download the certificate of analysis before the vial arrives and to verify that the batch number on the certificate matches the batch number printed on the vial label when it is received. Mismatches happen more often than they should, and they are much easier to resolve before the vial is opened than after an experiment has run. The same discipline applies whether the order is a single vial or a multi-batch series: documentation is only as good as its linkage to the physical goods.
For labs developing panels of metabolic peptides, ordering through the weight-management peptide category consolidates related compounds such as retatrutide, semaglutide, tesamorelin, and tirzepatide in one place, which simplifies record keeping and makes it easy to keep documentation standards consistent across the whole panel. Consistency of documentation is what turns a collection of vials into a defensible reagent library.
Practical Bench Notes for Research Buyers
The bench notes below are the distilled version of what careful laboratories do with either compound, and they apply to retatrutide vs semaglutide comparisons equally. First, aliquot before you reconstitute: decide the working concentration, reconstitute the entire vial at once, and divide the solution into single-use aliquots so that nobody re-thaws the stock. Second, log everything — the volume added, the solvent, the date, the person, and the batch number — because two different people reconstituting on two different days is a hidden variable in almost every failed reproducibility conversation.
Third, verify identity at receipt for a new batch, at least by inspecting the certificate’s mass-spec data, and ideally by running a quick analytical check if the lab has the capability. The cost of one failed measurement series dwarfs the cost of an identity check. Fourth, keep the peptide away from temperature excursions during transport: ask the supplier how the shipment is packed and whether cold-chain handling is documented, because lyophilized peptides are tolerant but not immortal, and an afternoon in a hot delivery van can change solubility behavior.
Fifth, write the storage plan before the first vial is opened. Decide where the stock lives, who has access, and what the freeze-thaw policy is, and write it into the lab protocol. Peptides that sit on a bench because nobody declared a storage policy degrade at different rates and quietly corrupt the very comparisons they were bought to support. Six, when in doubt about a certificate or a batch, contact the supplier with the batch number before using the material; a two-minute conversation upstream saves a two-week troubleshooting exercise downstream.
Building a Defensible Comparison Protocol
If the goal is a rigorous side-by-side study of retatrutide vs semaglutide, the protocol needs to be designed around the differences that actually matter. Start with matched conditions: both peptides reconstituted in the same vehicle, at concentrations normalized to peptide content rather than vial mass, and handled through identical storage, aliquoting, and thawing procedures. Any difference in treatment history between the two arms will be incorrectly assigned to the compounds themselves, and that error is extremely hard to argue with in review.
Next, define the endpoints in receptor terms. If the assay measures cyclic AMP, receptor activation, or downstream signaling, state which receptor systems are expected to contribute and justify why the chosen cell model expresses them. A single-receptor assay will favor the selective agonist and may miss the integrated response of the triple agonist; a multi-receptor assay will do the opposite. The protocol should say, in one sentence, what question the comparison is actually answering, because that sentence protects the whole experiment.
Finally, normalize and report honestly: include the assay system, the dose range, the vehicle, the batch numbers of both peptides, and the certificate data. An appendix that reproduces the relevant certificate fields is rarely criticized and frequently praised. A comparison protocol that can be re-run by an independent laboratory from the methods text alone is a comparison protocol worth publishing.
Common Pitfalls When Working with Both Compounds
The most common failure in this area is treating retatrutide vs semaglutide as interchangeable stock. They are not the same peptide, they do not engage the same receptor network, and a dose that is sensible for one compound may be meaningless for the other. The second most common failure is ignoring the certificate entirely: ordering both peptides, checking neither certificate, and discovering weeks later that the observed mass on one batch does not match the named peptide, or that the two batches have different stated purities. Certificates exist to be read, not filed.
A third pitfall is storage drift: keeping semaglutide frozen consistently while leaving the newer peptide at bench temperature between sessions, then puzzling over an apparent difference in stability that is actually a difference in handling. A fourth is dose math built on gross fill weight instead of peptide content, which silently shifts both arms of a comparison. A fifth is skipping the batch-number check between certificate and vial, which converts a documentation error into a data-quality problem the moment the vial is opened.
None of these pitfalls is exotic, and all of them are preventable with paperwork. The laboratories that get clean, reproducible data out of these compounds are rarely the ones with fancier instruments; they are the ones that treat documentation as part of the experiment. Read the certificate, log the handling, and let the peptide’s data speak.
Frequently Asked Questions
What is the main difference between retatrutide and semaglutide?
The main difference is the receptor profile. Semaglutide is a single-receptor incretin analog, while retatrutide is designed as a tri-agonist that also engages the glucagon axis. For laboratory work this changes the hypothesis, the control design, and the peptide form supplied.
Can retatrutide and semaglutide be combined in research?
Combination designs are possible but rarely clean. Because the compounds share an axis, attribution of an effect becomes difficult without controls that isolate each receptor. Laboratories usually run one compound per arm with separate batches, certificates and reconstitution records.
How do researchers verify retatrutide or semaglutide purity?
By the batch certificate of analysis. A useful certificate reports an HPLC purity percentage for the exact batch, identity confirmation by mass spectrometry, and a batch number that matches the vial label. Published lab reports add a second opinion on the same logic.
How should retatrutide and semaglutide vials be reconstituted?
Follow the standard lyophilized-peptide routine: refrigerate sealed vials until use, add bacteriostatic water down the inner wall, swirl gently, refrigerate the solution, and minimize freeze-thaw cycles. Record the exact volume and concentration on the label if the protocol demands reproducibility.
Retatrutide vs semaglutide: which has more published studies?
Semaglutide has the much larger publication base, built over many years of incretin research, while retatrutide represents a newer design with a smaller but rapidly growing literature. Both PubMed indexes are worth reading before choosing which compound fits a protocol.
Research use only: PeptideLabNova products are science-research reagents and are not intended or approved for human consumption. The information above is a factual summary of product and literature context for laboratory research buyers. PeptideLabNova products are supplied exclusively for research purposes, are not intended for human consumption, and nothing in this article constitutes medical, veterinary, or clinical advice.
